


You have a bottle of ketoconazole shampoo sitting in your bathroom, or you are thinking about buying one because your hair is getting thinner. The short answer up front: the active ingredient is proven against dandruff and against the flaking and itching of seborrheic dermatitis of the scalp, not against hair loss. Using it for hair loss is off-label, and the data behind that use are thin: the systematic review by Fields et al. (2020, Dermatologic Therapy) found only five human studies worldwide, with 318 participants in total. This article draws a clean line between what is proven, what is debated and what ketoconazole cannot do.
The key points at a glance
- ✓Ketoconazole is approved for dandruff and for tinea versicolor, not for hereditary hair loss
- ✓Nizoral A-D and the prescription 2% shampoos contain the same active ingredient, only at different strengths
- ✓What is documented is the effect on the scalp, and that is not a hair growth effect in its own right
- ✓Ketoconazole is not a DHT blocker and no substitute for minoxidil or finasteride
The table of contents shows where to find what. From there we work through the topic product by product and study by study.
Summary
- Does ketoconazole work against hair loss?
- What is ketoconazole, and what is Nizoral?
- What ketoconazole is approved for, and why hair loss is off-label
- How ketoconazole acts on the scalp and the hair
- What the studies on ketoconazole and hair loss show
- Ketoconazole or minoxidil? An honest comparison
- Using ketoconazole shampoo correctly
- Side effects, safety and the 2013 warnings
- Nizoral shampoo and hair loss: what user reports are really worth
- When the shampoo is not the answer: classifying hair loss correctly
- Conclusion: ketoconazole is a scalp treatment, not a hair growth treatment
- Frequently asked questions about ketoconazole for hair loss
- Sources
Does ketoconazole work against hair loss?
Ketoconazole for hair loss works on the scalp, not on the hair root. The evidence lies where the ingredient has actually been tested: with dandruff and with the flaking of seborrheic dermatitis of the scalp. As a treatment for hereditary hair loss in its own right, it is neither approved nor backed by meaningful studies.
The numbers show how far apart those two levels of evidence are. The safety of the 2% shampoo rests, according to its prescribing information (as of December 2022), on 22 clinical trials with 2,890 patients. For an effect against hair loss, by contrast, the systematic review by Fields et al. (2020) found only five human studies with a combined 318 participants.
The conclusion of that review is that topical ketoconazole is a promising adjunct or alternative therapy in androgenetic alopecia. In the same breath, the authors note that adequately powered randomized controlled trials are missing. Promising here means: not disproven, but not proven either.
For your decision, the second half of the answer matters more. If you have dandruff, itching or an irritated scalp, you are treating a real obstacle to hair growth. If your scalp is calm and flake-free and you use the shampoo purely against the hair loss, there is nothing documented that it could act on.
What is ketoconazole, and what is Nizoral?
Ketoconazole is the active ingredient, Nizoral one of the brand names it is sold under. Chemically it is a synthetic imidazole dioxolane derivative from the antifungal group (ATC code D01AC08). According to the prescribing information, it inhibits ergosterol biosynthesis in the fungal cell membrane and works that way against dermatophytes and yeasts, above all against Malassezia, formerly called Pityrosporum ovale.
Nizoral, Nizoral A-D and the generics: one active ingredient, different products
In the United States, ketoconazole shampoo is sold in two strengths. Nizoral A-D from Kramer Laboratories contains 1% ketoconazole; the 2% shampoos are sold as brand-name NIZORAL from Janssen Pharmaceuticals and as generics from ANI Pharmaceuticals and Padagis Israel Pharmaceuticals. Anyone searching for Nizoral and hair loss is, in effect, searching for ketoconazole.
The two strengths differ legally, not just in concentration. The 1% shampoo is available over the counter; it reached that status through a regular prescription-to-over-the-counter switch under its own new drug application (NDA 20-310, approved in 1997), not through the FDA’s dandruff monograph. The 2% shampoos remain prescription only and are marked Rx only on the label.

| Product | Strength | Dosage form | Approved for | Status in hair loss |
|---|---|---|---|---|
| Nizoral A-D (Kramer Laboratories) | 1% (10 mg/mL), over the counter | Shampoo | Controlling the flaking, scaling and itching of dandruff | Off-label |
| Ketoconazole Shampoo 2% (ANI Pharmaceuticals) | 2% (20 mg/mL), prescription only | Shampoo | Tinea (pityriasis) versicolor caused by Pityrosporum orbiculare (Malassezia furfur) | Off-label |
| Ketoconazole Shampoo 2% (Padagis Israel Pharmaceuticals, ANDA 076419) | 2% | Shampoo suspension, 120 mL | Tinea (pityriasis) versicolor | Off-label |
| NIZORAL 2% Shampoo (Janssen Pharmaceuticals) | 2% | Shampoo | Tinea (pityriasis) versicolor, the only indication in the current label | Off-label |
1% or 2%? What the difference in strength means
In the United States, over-the-counter and prescription ketoconazole-shampoos The primary studies in this article, Piérard-Franchimont 1998 and Khandpur 2002, looked at 2% ketoconazole; the reviews by Fields 2020 and Gupta 2025 pool trials across different strengths.
The 1% version is often described online as an over-the-counter product under the FDA’s dandruff monograph. That is not the case. Ketoconazole is not one of the active ingredients permitted there; 21 CFR Part 358, Subpart H, lists coal tar, pyrithione zinc, salicylic acid, selenium sulfide and sulfur. Nizoral A-D reached drugstore shelves through a regular prescription-to-over-the-counter switch under a full new drug application instead.
In practice that means: cosmetic anti-dandruff products from the drugstore aisle do not come in the strength the studies looked at. If you want the version that was actually tested, that is the 2% prescription shampoo, used according to its prescribing information.
What ketoconazole is approved for, and why hair loss is off-label
Ketoconazole is approved for conditions of the scalp and the skin, not for hair loss, and the approved uses differ from product to product. The over-the-counter 1% shampoo is approved to control the flaking, scaling and itching of dandruff. The 2% prescription shampoos carry a narrower indication: their current FDA label covers the treatment of tinea (pityriasis) versicolor. Other ketoconazole preparations can cover further uses. What counts is always the label of the product in your hand. Androgenetic alopecia appears in none of these approvals.
What does off-label use mean with ketoconazole?
Off-label use with ketoconazole means using an approved medicine outside the uses for which it was tested and cleared. What is approved are scalp and skin conditions such as dandruff and tinea versicolor, not hereditary hair loss. Three things follow from that.
Off-label use of ketoconazole: three concrete consequences
- ✓No tested efficacy: With hair loss as the goal, the effect was never examined in the approval process, and it therefore does not appear in the prescribing information.
- ✓Off-label: Whether use outside the approved indication makes sense is for a physician to decide. There is no proof of efficacy against hair loss to support it.
- ✓Responsibility shifts: Responsibility for the use lies with you, or with the physician supervising it, which is why a short conversation is worth having.
Whether you are in off-label territory at all comes down to one detail. If you have dandruff and treat it for that reason, you are using the product within its approved use and may see a benefit for your hair along the way. If you have no scalp finding and wash purely because of the hair loss, you are entirely outside the approved use.
That is not an American peculiarity. The labeled uses are narrow in every market: in the United States the 1% shampoo is cleared for dandruff and the 2% shampoo for tinea versicolor, and hair loss appears on neither label. Using ketoconazole against hair loss is off-label here just as it is elsewhere.
How ketoconazole acts on the scalp and the hair
The documented route: through the scalp
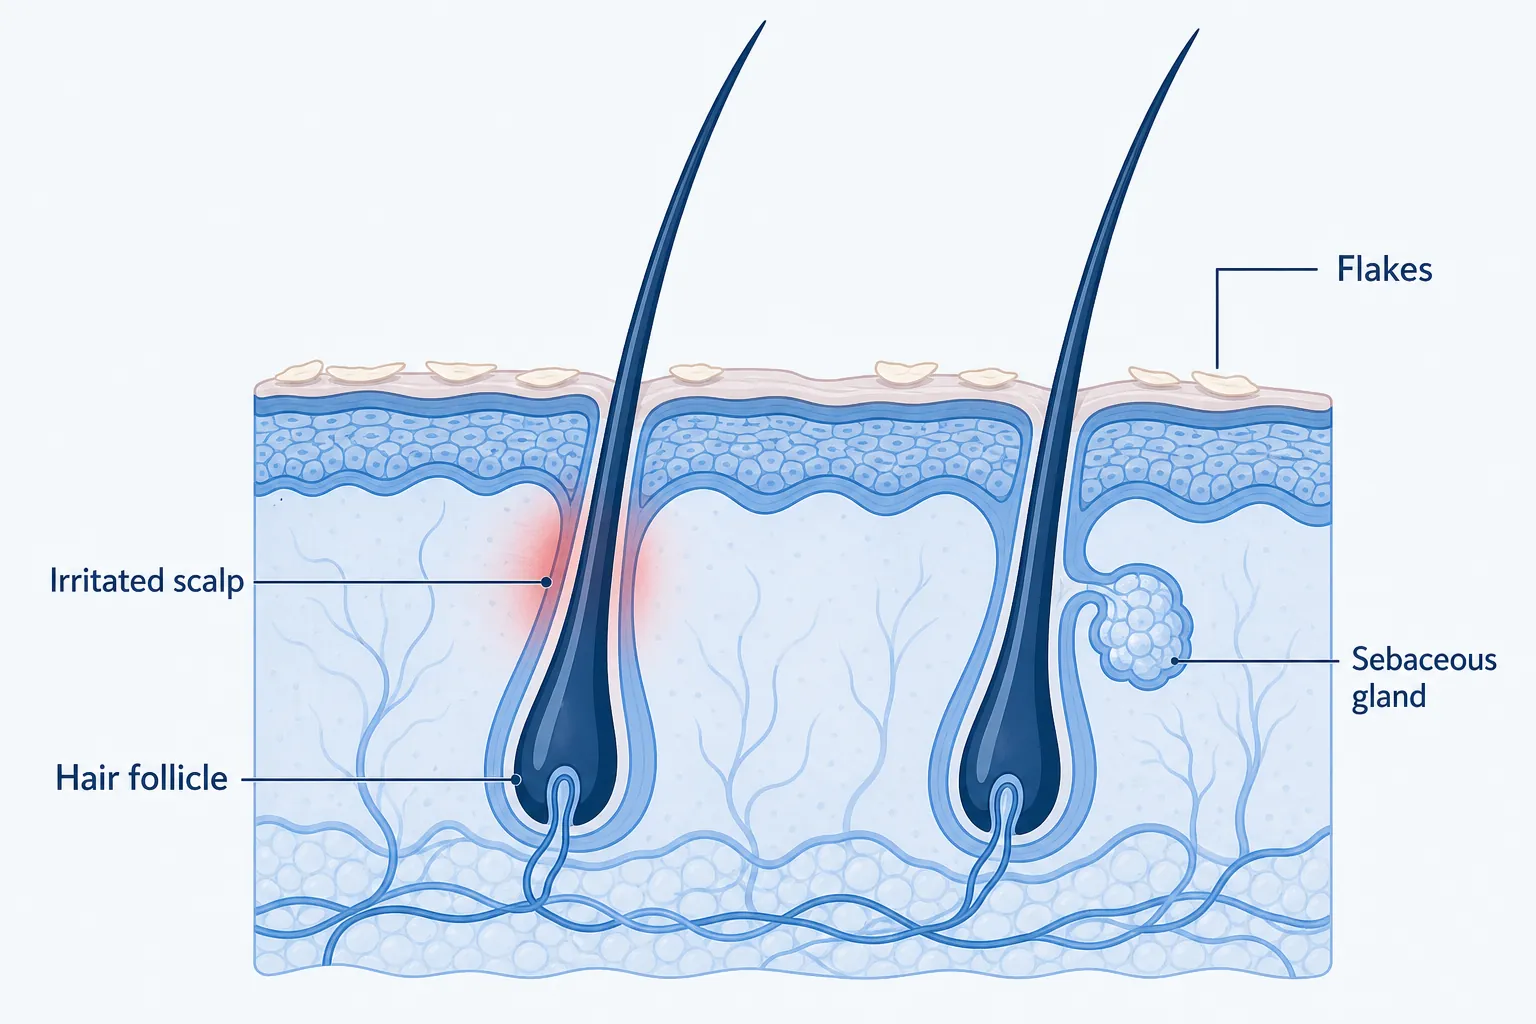
The documented route of action for ketoconazole runs through the scalp microbiome. Malassezia yeasts are part of the normal scalp flora, but they can contribute to seborrheic dermatitis with flaking, micro-inflammation and itching. According to the prescribing information, ketoconazole inhibits the ergosterol biosynthesis of these yeasts and brings the Malassezia balance back to a quieter state.
From there comes the indirect link to the hair: a chronically irritated, inflamed scalp is an unfavorable environment for hair growth. That is exactly where Gupta et al. (2025, JEADV Clinical Practice) come in when they describe ketoconazole shampoo as reducing chronic scalp inflammation that would otherwise damage hair follicles. That is not a hair growth drug effect; it is an improvement in the conditions for growth.
The hypothetical route via 5-alpha-reductase
A mild antiandrogenic effect directly on the scalp is discussed as well. Gupta et al. (2025) cite antiandrogenic properties of ketoconazole as a possible contribution to less hair loss, limited to the short contact time the shampoo has with the skin. This route is not proven; it is a plausible hypothesis and is treated as one in the literature.
A systemic effect like the one seen with oral finasteride is explicitly not what is meant. The prescribing information for 2% ketoconazole shampoo notes that no ketoconazole was detectable in plasma after use on the scalp and that percutaneous absorption is negligible.
A common misunderstanding: ketoconazole is not a DHT blocker
Plenty of advice pages file ketoconazole shampoo under the heading DHT blocker and leave it there. That does not hold up. The active ingredient is approved as an antifungal, and an antiandrogenic effect is discussed only as a locally limited hypothesis, not as a demonstrated mechanism.
The widely circulated claim that ketoconazole lowers DHT on the scalp by 12 to 16 percent after four weeks could not be found in any of the primary sources reviewed, neither in the studies nor in the prescribing information. Treat that number as an unsourced internet figure, not as a measurement.
What the studies on ketoconazole and hair loss show
The evidence on ketoconazole and hair loss consists of a handful of small papers, none of which is a randomized, placebo-controlled proof of efficacy. That is not a judgment but the state of play recorded by the systematic review by Fields et al. (2020, Dermatologic Therapy) after screening 47 papers: seven included studies, five of them in humans with 318 participants.
The oldest and most quoted paper comes from Piérard-Franchimont et al. (1998, Dermatology). It has two parts. In the first, 27 men with hereditary hair loss on the crown used nothing but 2% ketoconazole shampoo for 21 months, while another 12 used an unmedicated shampoo. The endpoint was the pilary index, the product of the anagen rate and the hair shaft diameter. It rose in the ketoconazole group and fell in the control group. That was not a pure hair density measurement, and the study was neither randomized nor placebo-controlled.
The second part is where the well-known line comes from, that ketoconazole works much like minoxidil. That claim rests on eight men, four per group, over six months. In both groups the hair shaft diameter increased by around 7 percent. Four men against four cannot establish equivalence, and yet that is exactly the claim made online again and again.
Khandpur et al. (2002, Journal of Dermatology) compared four treatment groups with a total of 100 men over one year. The best result came from finasteride plus minoxidil (36 patients), followed by finasteride plus ketoconazole shampoo (10 patients). Important for context: there was no ketoconazole-only group, so the ingredient was tested only as an add-on to finasteride.
The most recent paper is the review by Gupta et al. (2025, JEADV Clinical Practice). For dandruff and seborrheic dermatitis it rates ketoconazole shampoo as superior to selenium sulfide, corticosteroids and zinc pyrithione in several double-blind randomized trials. For androgenetic alopecia it calls the shampoo a possible addition to minoxidil and finasteride, not a replacement.
The strongest signal is an absence. The European S3 guideline on the treatment of androgenetic alopecia by Kanti et al. does not mention ketoconazole anywhere and therefore does not rate it either. An ingredient that does not appear in the authoritative guideline is not a second-line option; it is simply unrated.
Before you draw a conclusion from that, it is worth taking one step in between: the thin evidence says something about the ingredient, nothing about your cause. Whether the scalp, a diffuse trigger or your genetics is behind it determines what can help in the first place. An overview of the causes of hair loss helps you sort that out, and the pattern-by-pattern comparison is in the classification table further down.
| Study and year | Design and participants | Finding | What the study does not show |
|---|---|---|---|
| Piérard-Franchimont 1998, part 1 | Not randomized, no placebo; 39 men, 27 of them on ketoconazole shampoo and 12 on a control shampoo, over 21 months | Pilary index (anagen rate × hair shaft diameter) rose on ketoconazole and fell in the control group | No comparison with minoxidil, no randomization, no blinding |
| Piérard-Franchimont 1998, part 2 | Very small subsample; 8 men, 4 on ketoconazole versus 4 on minoxidil 2%, over 6 months | Hair shaft diameter increased by around 7% in both groups | No equivalence with minoxidil; with 4 against 4 participants it cannot be generalized |
| Khandpur 2002 | Open, randomized, 100 men in 4 groups over 1 year | Best effect with finasteride plus minoxidil, then finasteride plus ketoconazole | No ketoconazole monotherapy, and therefore no evidence for the shampoo on its own |
| Fields 2020, systematic review | 7 included papers, 5 of them human studies with 318 participants | Classified as a promising adjunct or alternative therapy | No adequately powered randomized trials |
| Gupta 2025, review | Most recent overview of ketoconazole in hair care | Possible addition to minoxidil or finasteride, mild local effect discussed | No demonstrated equivalence, no recommendation for approval |
Ketoconazole or minoxidil? An honest comparison
Ketoconazole and minoxidil are not alternatives on an equal footing; they sit on different levels of approval and evidence. Minoxidil is approved for androgenetic alopecia and carries the highest level of evidence in the European S3 guideline by Kanti et al. Ketoconazole is approved for scalp conditions and is off-label in hair loss.
For a sense of scale: the same guideline puts the proportion affected at up to 80 percent of Caucasian men and 42 percent of women, rising with age. For a condition this common and this slow to progress, the choice of ingredient is no small matter, and a shampoo with an unclear evidence base does not replace an approved medicine.
For the combination there is one factual note, not a plan. The label for minoxidil explicitly calls for application to a completely dry scalp, because damp skin dilutes the concentration and can increase absorption into the bloodstream. So if you use both, you wash first, let everything dry completely and discuss the combination with a physician beforehand.
For everyday use that mainly means keeping wash day and the minoxidil application apart. If you use the ketoconazole shampoo in the morning and apply minoxidil in the evening to a scalp that is dry by then, you meet the requirement on the label without waiting around in the bathroom. Since the shampoo is only meant to be used twice a week, this coordination affects two days of the week anyway.
A pharmacological interaction between the two is neither documented nor ruled out: the prescribing information for 2% ketoconazole shampoo notes that no interaction studies have been carried out. That is not the same as an all-clear, and another reason not to start the combination on your own.
| Criterion | Ketoconazole 2% topical | Minoxidil topical | Finasteride oral |
|---|---|---|---|
| Approval for hereditary hair loss | No, off-label | Yes | Yes, in men |
| Site of action | Scalp, local | Hair follicle and scalp | Systemic, 5-alpha-reductase type II |
| Mechanism | Antifungal, with a debated mild local antiandrogenic effect | Widens blood vessels, extends the anagen phase | Lowers systemic DHT |
| Strength of the evidence | 5 small human studies, no adequately powered randomized trial | Highest level of evidence in the S3 guideline | High evidence, guideline standard in men |
| Role in treatment | Supportive at most | First-line treatment | First-line treatment in men |
Does ketoconazole work against hair loss in women?
For women, ketoconazole in hair loss sits exactly where it sits for men, only on an even thinner set of data. The approval of the 2% shampoos applies regardless of sex and covers skin and scalp conditions, not hair loss. There is no sex-specific statement of efficacy for the hair.
The reason is in the studies themselves: Piérard-Franchimont et al. (1998) studied 39 men, Khandpur et al. (2002) 100 men. The two most quoted clinical papers on ketoconazole and hereditary hair loss therefore included men only. Nothing can be transferred from that to women, in either direction.
The difference lies with the approved medicines. The European S3 guideline by Kanti et al. gives minoxidil the highest level of evidence in women as well, while oral finasteride is recommended there as a treatment in men. Women dealing with hair loss in women therefore start from a different place than a man with the same finding.
In pregnancy and while breastfeeding, the note from the safety section further down applies: controlled studies are missing, and according to the prescribing information no ketoconazole was detectable in plasma after use on the scalp. A short conversation with your physician, pharmacist or midwife is still the better route than deciding on your own.
What to do when ketoconazole alone is not enough
When ketoconazole alone is not enough, the next step leads to the ingredients approved for hair loss, not to the next shampoo. On the evidence, ketoconazole remains a possible addition, which is how Gupta et al. (2025) classify it too. The mainstay of treatment lies elsewhere.
Where things go from here
- ✓The scalp stays irritated: If flaking and itching do not improve on the schedule in the prescribing information, the next step is a dermatologist, not a longer contact time.
- ✓The pattern is progressing: With receding temples and a thinning crown, minoxidil is the topical with the highest level of evidence in the European S3 guideline.
- ✓Men with a hereditary pattern: Oral finasteride is the treatment recommended in the same guideline, available on prescription and with a side effect profile of its own.
- ✓Looking for the DHT lever: What is documented for this group of ingredients and what remains marketing is broken down in our overview of DHT blockers.
- ✓Other shampoo ingredients: Caffeine, zinc pyrithione and selenium sulfide each have their own evidence base, of varying strength; Gupta et al. (2025) see ketoconazole ahead of zinc pyrithione and selenium sulfide in dandruff. The comparison is in our overview of shampoo for hair loss.
None of that establishes a general order of priority. Which of these routes makes sense depends on the cause, on your age and on any existing conditions, and every one of these ingredients belongs in a conversation with a physician. Further down, the classification table helps you sort out your own pattern first.
Using ketoconazole shampoo correctly
Ketoconazole shampoo is not used like a normal shampoo but on a fixed schedule with a contact time. The prescribing information for 2% ketoconazole shampoo specifies around 5 mL of shampoo on a dampened scalp, 3 to 5 minutes of contact time, thorough rinsing and an application twice a week for 2 to 4 weeks.
After that comes the maintenance phase, with one application every 1 to 2 weeks. Other ketoconazole shampoos come with schedules of their own, and the over-the-counter and the prescription strength are not used in the same way. Stick to the schedule for the product in your hand, not to an averaged rule of thumb.
Application in four steps (per the prescribing information for 2% ketoconazole shampoo)
- ✓Dampen hair and scalp thoroughly with water.
- ✓Massage about 5 mL of shampoo gently over the whole scalp, not just into the lengths of your hair.
- ✓Leave on for 3 to 5 minutes, then rinse thoroughly.
- ✓Apply twice a week for 2 to 4 weeks, then every 1 to 2 weeks as maintenance.

One point that regularly gets lost in forums: these figures apply only to topical use as a shampoo or solution. They cannot be transferred to ketoconazole tablets, whose approval as an antifungal has been suspended in the EU since 2013 and whose use the FDA sharply restricted in the same year. More on that below in the section on safety and the 2013 warnings.
Equally widespread is the advice to leave the shampoo on longer or overnight to boost the supposed DHT effect. There is no basis for that. The prescribing information states a fixed contact time, and longer contact mainly raises the risk of irritation, burning and contact dermatitis, with no documented extra benefit.
On the time frame: flaking and itching typically improve within a few weeks on the schedules in the prescribing information. Any effect on the hair would take months to judge, because of the hair cycle and the fact that the growth phase of a single hair lasts years.
The most common reasons people write the shampoo off as useless are mechanical: too short a contact time, irregular use, judging the result after just two weeks, and starting several products at once, which makes attribution impossible.

Side effects, safety and the 2013 warnings
The side effects of ketoconazole shampoo are mostly local. The prescribing information for 2% ketoconazole shampoo draws on safety data from 2,890 patients in 22 clinical trials; not a single side effect occurred at a frequency of 1 percent or more. The most common are reactions at the application site such as redness, irritation and itching.
| Frequency | Documented side effects |
|---|---|
| Uncommon (1 in 1,000 to 1 in 100) | Alopecia, dry skin, changed hair texture, rash, burning sensation of the skin, folliculitis, increased tear flow, application site reactions such as redness, irritation and itching |
| Rare (1 in 10,000 to 1 in 1,000) | Hypersensitivity, taste disturbance, eye irritation, acne, contact dermatitis, skin disorders, skin exfoliation, pustules at the application site |
| Frequency not known | Angioedema, urticaria, hair discoloration |
One line in this table deserves an explanation of its own. Alopecia, that is hair loss, is listed as an uncommon side effect of ketoconazole shampoo. A product that many people use against hair loss can, in uncommon cases, cause it. That belongs in an honest assessment, uncomfortable as it is.
More hair in the brush: breakage or genuine loss?
Initial shedding, of the kind described for minoxidil, is not documented for ketoconazole in the prescribing information reviewed. The alopecia listed there is an uncommon individual event, not a typical starting phenomenon for everyone. If you see more hair in the first few weeks, do not dismiss it either: the prescribing information lists alopecia as a possible side effect, and irritation or a contact allergy can be behind it too. If the increase persists, it belongs in a medical assessment rather than in further treatment.
The more plausible explanation is breakage from dryness. Medicated shampoos dry out the hair shaft more than conditioning shampoos do; broken hairs are shorter and have no whitish root end, while shed hairs do. A conditioner in the lengths, not on the scalp, usually solves the problem.

Two further points from the labels, each specific to the individual product: hair discoloration is listed as a side effect with unknown frequency, which can matter with colored, bleached or permed hair. The minimum age differs from product to product, so check the label of the product you are using instead of assuming a general rule.
For pregnancy and breastfeeding, the prescribing information states that adequate controlled studies are not available; data from a limited number of exposed pregnancies show no signs of adverse effects, and no ketoconazole was detectable in plasma after use on the scalp. A short conversation with your physician or midwife still makes sense.
None of the prescribing information reviewed says anything about use after a hair transplant. Freshly transplanted scalp is a special case for which there can be no blanket clearance. Ask the clinic treating you; they know how your recovery is going.
Shampoo is not a tablet: what the 2013 warnings actually cover
In 2013, in a procedure under Article 31 of Directive 2001/83/EC, the European Medicines Agency (EMA) recommended suspending the marketing authorizations for oral ketoconazole medicines used as antifungals Use in Cushing’s syndrome is not covered by this and remains authorized in the EU. The reason was liver damage up to and including liver failure, which occurred more often and more severely than with other antifungals, usually 1 to 6 months after the start of treatment and also at the recommended daily dose of 200 mg. In the United States, the FDA issued a Drug Safety Communication on July 26, 2013, limiting the use of oral Nizoral (ketoconazole) tablets for the same reasons; the label for the tablets carries a boxed warning on liver injury and drug interactions.
This measure applies to tablets only. Shampoo, solution and cream are not affected, because according to the prescribing information there is no relevant systemic uptake through the scalp. Nor is it a blanket ban on oral use: for the treatment of Cushing’s syndrome, oral ketoconazole remains authorized in the EU, a separate indication under close medical supervision.
Nizoral shampoo and hair loss: what user reports are really worth
If you go looking for experiences with Nizoral shampoo in hair loss, you mostly find two camps: enthusiastic reports of thicker hair and equally firm disappointment. Both camps can be right, because they describe different starting points. For methodological reasons, user reports are particularly unreliable on this topic.
Four reasons explain almost every discrepancy between two reports on the same shampoo.
Why user reports on ketoconazole shampoo differ so widely
- ✓No control arm: Nobody can compare their own treated head with their own untreated head.
- ✓Seasonal shedding: The amount of hair shed varies over the year, independently of any treatment.
- ✓Parallel treatments: Many people start several products at once, which makes attribution impossible. That is exactly what prevented a statement about ketoconazole alone in Khandpur et al. (2002), where the ingredient was only tested together with finasteride.
- ✓Expectations: Anyone who deliberately buys and uses a product judges their own head differently than a neutral observer would.
The most important reason, though, is a different one. Anyone who actually had dandruff or seborrheic dermatitis experiences a real and well-documented improvement in the condition of the scalp. Less itching, less flaking, less scratching, hair that feels fuller overall. In a user report, that real effect easily turns into a story about hair growth, even though it is the scalp that got better and not the hair density.
What can plausibly be reported, on the evidence, is this: a calmer scalp, less flaking, less itching and subjectively better-feeling hair. What is not documented is measurable regrowth on areas that are already bald. There is no basis for that claim in Fields et al. (2020), in Gupta et al. (2025) or in the prescribing information.
Rather than going by other people’s reports, you are better off tracking your own progress. The eight-week grid below shows what you can actually judge, and when. Two things take precedence: the prescribing information calls for a conversation with a physician if nothing improves after about four weeks of approved use. And an observation period is no reason to postpone a necessary assessment. If something gets worse, if the scalp becomes irritated or if noticeably more hair falls out, see a doctor sooner.
| Point in time | What to look at | What a real change would be | What you cannot judge yet |
|---|---|---|---|
| Before you start | Set the routine from the prescribing information: frequency, contact time, thorough rinsing. Photo in the same light, at the same angle, with dry hair. Note flaking and itching | Nothing, this is the starting point | Everything |
| Week 2 | Flaking, itching, redness. Be honest about whether you really kept to the contact time and the frequency | Noticeably less flaking and less itching | Hair density and the amount of hair being shed |
| Week 4 | Scalp appearance, oiliness, tolerance | Calmer scalp, no burning, no irritation | Hair growth |
| Week 8 | Second photo under the same conditions | Scalp calm and staying that way, hair at best unchanged and stable | Whether new hair is growing on bald areas |
| After week 8 | Take stock | Scalp problem solved means the goal is met. Hair still getting worse means: have the cause assessed by a physician | An effect against hereditary hair loss |

When the shampoo is not the answer: classifying hair loss correctly
Whether ketoconazole can do anything for you at all depends on the type of hair loss you have. The ingredient is approved for scalp conditions caused by fungi. With diffuse hair loss and with hereditary hair loss it changes nothing about the cause, and it does not appear in the European S3 guideline.
Three patterns can be told apart reasonably well with a little observation. Scalp-related means: flaking, itching, a reddened or oily scalp. Diffuse means: even thinning across the whole head, often from deficiencies, hormones, medication or stress. Hereditary means: receding temples and a thinning crown over years, in a typical pattern.
Some findings belong with a physician regardless: round bald patches, a painful or scarring scalp, sudden heavy hair loss and a rash on the scalp. What matters here is that treating with a shampoo does not end up masking a finding that needs treatment in its own right.

| What you observe | More likely points to | What ketoconazole can do there | Sensible next step |
|---|---|---|---|
| Flaking, itching, a reddened or oily scalp, hair shedding diffusely along with it | Scalp condition, seborrheic dermatitis | This is where the documented effect lies; for dandruff it is an approved use | Use the product according to its label, and see a dermatologist if there is no improvement |
| Even thinning across the whole head, noticeably more hair in the brush and the drain | Diffuse hair loss, telogen effluvium | Nothing about the cause, at most scalp care | Have the causes checked: blood work, medications, thyroid |
| Receding temples, thinning crown, a pattern over years | Androgenetic alopecia | Supportive at most, not an approved treatment for this form | Discuss approved ingredients with a physician and have the pattern classified |
| Bald areas that have not changed for years | Possibly permanently lost follicles; only a physician can judge that, and scarring alopecia in particular looks unremarkable from the outside | Nothing, no hair grows there anymore | Have the pattern classified, then consider a hair transplant |
| Round bald patches, pain, scarring, sudden heavy loss | A finding that needs treatment | Use can mask the finding | Have it assessed promptly, do not treat it yourself |

One limit stays the same with every shampoo: no shampoo brings permanently lost follicles back. Whether the follicles on a bald area really are lost, however, cannot be decided in front of the mirror. Scarring alopecias in particular look unremarkable from the outside and belong in a dermatological assessment before anything is planned. Once that assessment is done and the follicles really are permanently lost, a hair transplant can grow your own hair there again. Your own follicles are taken from the back of the head (FUE) and placed with the DHI technique, under local anesthesia, with every step signed off by a physician.
Before that even becomes a question, there is the classification. Our free hair analysis is exactly that: a visual pattern analysis based on your photos, which classifies the type of hair loss you have. It does not replace a blood test or a dermatological examination, and it regularly ends in a no: based on our own review, we turn down around 40 percent of inquiries because a transplant is not the right answer.
Conclusion: ketoconazole is a scalp treatment, not a hair growth treatment
Ketoconazole for hair loss is a sensible choice when the scalp is the problem. Against dandruff and seborrheic dermatitis the ingredient is well studied and, according to Gupta et al. (2025), superior to several other anti-dandruff ingredients. That removes a genuine obstacle to healthy hair growth.
An approved hair growth treatment it is not. The evidence for that consists of five small human studies with 318 participants in total, ketoconazole does not appear in the European S3 guideline, and the prescribing information even lists alopecia as an uncommon side effect. As an addition it may have its place; as a substitute for approved ingredients it does not.
In practice that means: treat a flaky, irritated scalp according to the prescribing information and give it a few weeks. If the hair loss is unchanged after that, or if it progresses in a pattern, the cause is probably elsewhere. That cannot be proven from the course alone, since the hair cycle lags and more than one cause at a time is possible. The next step is therefore a medical assessment, not the next shampoo.
Frequently asked questions about ketoconazole for hair loss
Does ketoconazole help with hereditary hair loss?
No. For hereditary hair loss, ketoconazole is neither approved nor supported by evidence. The systematic review by Fields et al. (2020) found only five human studies with 318 participants and no adequately powered randomized trial, and the European S3 guideline by Kanti et al. does not mention the ingredient. What is documented is the effect against dandruff and the flaking of seborrheic dermatitis of the scalp.
Can ketoconazole shampoo stop hair loss?
There is no evidence for that. If a flaky, inflamed scalp is disturbing hair growth, treating that obstacle can improve the situation; whether it also acts on the hereditary course itself has not been studied adequately. The available studies are small and methodologically weak, which leaves the question open rather than proving the ingredient useless.
What is Nizoral, and is it the same as ketoconazole?
Nizoral is a brand name, ketoconazole the active ingredient in it. Nizoral A-D from Kramer Laboratories contains 1% ketoconazole and is sold over the counter; the 2% prescription shampoos, brand-name NIZORAL from Janssen and generics from ANI Pharmaceuticals and Padagis, contain the same ingredient at twice the strength.
Do you need a prescription for ketoconazole shampoo?
In the United States it depends on the strength. The 1% shampoo is available over the counter, while the 2% shampoos are prescription only and are marked Rx only. The over-the-counter status of the 1% product goes back to a prescription-to-over-the-counter switch under its own new drug application, not to the FDA’s dandruff monograph.
Is a 1 percent shampoo enough, or do I need 2 percent?
The primary studies quoted here (Piérard-Franchimont 1998, Khandpur 2002) looked at 2% ketoconazole; the reviews also pool other strengths. In the United States the 1% shampoo is the one you can buy without a prescription, and it is approved to control dandruff. Which strength you can get therefore depends on the prescription status, not on the hair loss question: neither strength is approved for hair loss.
Is ketoconazole a DHT blocker?
No, ketoconazole is approved as a topical antifungal. Gupta et al. (2025) discuss antiandrogenic properties only as a locally limited hypothesis for the short contact time on the scalp. The widely circulated figure of a 12 to 16 percent drop in DHT could not be found in any primary source.
Ketoconazole or minoxidil: which is better?
The two are not on the same level. Minoxidil is approved for androgenetic alopecia and carries the highest level of evidence in the European S3 guideline, while ketoconazole is off-label in hair loss. The often quoted tie comes from a sub-experiment with eight men, four per group.
Can women use ketoconazole shampoo against hair loss?
The approval of the 2% shampoos applies regardless of sex, but it covers skin and scalp conditions and not hair loss. There is no documented statement of efficacy for women, because Piérard-Franchimont et al. (1998) and Khandpur et al. (2002) studied men only. For hereditary hair loss in women, the European S3 guideline gives minoxidil the highest level of evidence.
How often should ketoconazole shampoo be used?
The prescribing information for 2% ketoconazole shampoo specifies twice a week for 2 to 4 weeks with a contact time of 3 to 5 minutes, then every 1 to 2 weeks as maintenance. Daily use is not intended, and the schedule differs slightly from product to product.
How long does it take to see anything?
Flaking and itching usually improve within a few weeks on the schedules in the prescribing information. A change in the hair would take months to judge because of the hair cycle, and an independent hair growth effect is not documented in any case.
Does more hair fall out at the start?
Initial shedding, of the kind described for minoxidil, is not documented for ketoconazole in the prescribing information reviewed. It is possible that the hairs have broken off from dryness; those are shorter and have no whitish root end. That is not certain, though: the prescribing information lists alopecia as a possible side effect. If the increase persists or the scalp is irritated, stop the product and have it assessed by a physician.
Can ketoconazole itself cause hair loss?
It is possible: alopecia is listed in the prescribing information as an uncommon side effect, meaning in 1 in 1,000 to 1 in 100 users. If hair loss increases noticeably during use, speak to your physician or pharmacist.
What side effects does ketoconazole shampoo have?
Mostly local ones: dry skin, a burning sensation of the skin, irritation, redness and itching at the application site, plus contact dermatitis or hypersensitivity. The prescribing information puts these reactions in the “uncommon” category, meaning at least 1 in 1,000 and fewer than 1 in 100 of those treated. According to the same source, the safety data come from 22 clinical trials with 2,890 patients, in which no side effect reached a frequency of 1 percent.
Does ketoconazole also come as tablets, and is it safe to take them?
The authorizations for oral ketoconazole medicines have been suspended in the EU since 2013, after the EMA assessed severe liver damage in an Article 31 procedure, and the FDA sharply limited their use in the same year. The measure concerned use as an antifungal. It is not a blanket ban on every oral use: for the treatment of Cushing’s syndrome, oral ketoconazole remains authorized in the EU, a separate indication under close medical supervision. Against hair loss, ketoconazole tablets are never an option; shampoo and solution are not affected by the measure.
Can you use ketoconazole shampoo after a hair transplant?
There is no blanket clearance for that; none of the prescribing information reviewed addresses freshly transplanted scalp. Before you use a medicated shampoo, ask the clinic treating you; they know how your recovery is going.
Sources
Sources used (as of September 2026)
- Fields JR, Vonu PM, Monir RL, Schoch JJ (2020): Topical ketoconazole for the treatment of androgenetic alopecia. A systematic review. Dermatologic Therapy 33(1):e13202. View source
- Piérard-Franchimont C, De Doncker P, Cauwenbergh G, Piérard GE (1998): Ketoconazole shampoo, effect of long-term use in androgenic alopecia. Dermatology 196(4):474–477. View source
- Khandpur S, Suman M, Reddy BS (2002): Comparative efficacy of various treatment regimens for androgenetic alopecia in men. Journal of Dermatology 29(8):489–498. View source
- Gupta AK, De Doncker P, Talukder M (2025): Role of topical ketoconazole in therapeutic hair care beyond seborrhoeic dermatitis and dandruff. JEADV Clinical Practice 4(4):710–718. View source
- Kanti V, Messenger A, Dobos G et al.: Evidence-based (S3) guideline for the treatment of androgenetic alopecia in women and in men. European Dermatology Forum, JEADV. View source
- Prescribing information, Ketoconazole Shampoo 2%, as of December 2022 (Padagis Israel Pharmaceuticals Ltd., DailyMed). View source
- Drug Facts label, Nizoral A-D (ketoconazole 1%) shampoo (Kramer Laboratories, Inc.). View source
- EMA (2013): Ketoconazole, Article 31 referral, Annex II (oral dosage forms). View source
- FDA (2013): Drug Safety Communication — FDA limits usage of Nizoral (ketoconazole) oral tablets (archived copy). View source
This article is for information and does not replace medical advice, diagnosis or treatment. Medicines are used according to their current labeling; if hair loss persists or your scalp shows an unusual finding, please see a physician.

Dr. Imad Moustafa
Hair transplant specialist